
- Have any questions?
- 085913 90567
- drgeorgechestdiseases@gmail.com

What Is Tracheal Stenosis and How Is It Treated?

What Is a Thymoma and Does It Need Surgery?
July 1, 2026
Surgery vs Radiation: Which for Early Stage Lung Cancer?
July 7, 2026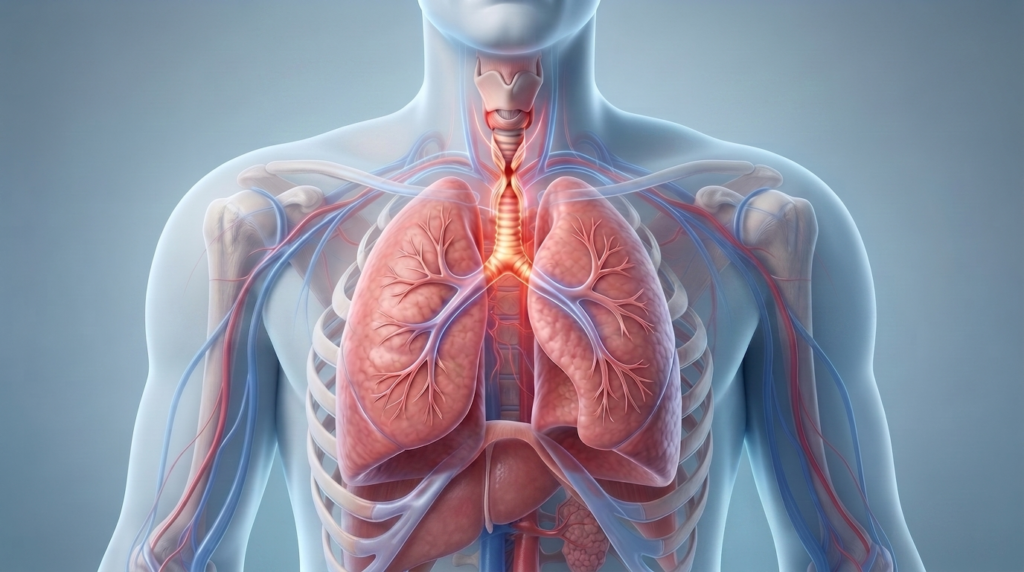
The windpipe narrows. That’s tracheal stenosis. Usually it’s scar tissue left behind by a breathing tube or a tracheostomy, though tumours or direct injury to the neck or chest can cause it too. Timing is what makes this condition hard to catch early. Nothing shows until the airway’s lost close to two thirds of its width. By the time symptoms are noticed, the narrowing is often more advanced than expected.
According to Dr. George Karimundackal, a leading Thoracic Surgeon in Mumbai, “People spend months on asthma inhalers before anyone checks the windpipe itself. The breathing sound changes first, a high pitched noise going in, and that’s what gets missed almost every time. Look at the trachea directly and the answer’s usually there within minutes.”
What Are the Symptoms of Tracheal Stenosis?
These get mistaken for asthma or bronchitis early on. That’s what delays diagnosis.
- Stridor: a harsh, high pitched sound on breathing in. The clearest early sign. Also the one missed most.
- Breathlessness on exertion: breathing gets harder with activity, even if it’s fine at rest.
- A cough that won’t clear: dry, persistent, no obvious infection driving it.
- Poor response to inhalers: if asthma treatment isn’t working, that points toward the airway structure, not the lungs.
Real narrowing has to build up before any of this shows. Plenty of people carry a partly blocked windpipe for months without realising it. Breathing problems that don’t respond to treatment need the airway checked directly, through a proper tracheal surgery evaluation rather than more inhalers.
How Is Tracheal Stenosis Treated?
Dr. George Karimundackal, MBBS, MS (General Surgery), MCh (Surgical Oncology), MRCS Edinburgh, is Director of Thoracic Surgery at Nanavati Max Super Speciality Hospital, Mumbai. Few surgeons in India take on tracheal work. He’s among the more experienced in Mumbai, having handled cases from routine dilations to complex resections at the lower trachea. He’s published anaesthesia protocols for tracheal resection too, which says something about the planning these cases need before anyone reaches the operating table. Every airway case goes through the full surgical and anaesthesia team before a plan is set.
Why Choose Dr. George Karimundackal?
Dr. George Karimundackal, MBBS, MS (General Surgery), MCh (Surgical Oncology), MRCS Edinburgh, is Director of Thoracic Surgery at Nanavati Max Super Speciality Hospital, Mumbai. With over 15 years as a thoracic surgeon, more than 1,000 minimally invasive thoracic procedures performed, and a prior role as Professor of Thoracic Surgery at Tata Memorial Hospital, he brings the depth of subspecialty training and case volume that complex thoracic conditions demand.
Frequently Asked Questions
Most cases follow prolonged intubation or a tracheostomy, where scar tissue narrows the airway as it heals. Tumours, injury, and inflammatory conditions are less common causes.
Mild, short segment stenosis often responds to endoscopic dilation. Longer or recurrent stenosis usually needs surgical resection for a lasting result.
Published series report success rates between 71 and 96 percent, depending on stenosis length, prior treatment, and overall patient health.
Noisy breathing or stridor, breathlessness on exertion, and a cough that does not improve with asthma treatment are common early signs.
